




Pull to refresh
Logo
FDA approves Jaypirca for previously untreated CLL/SLL

FDA approves Jaypirca for previously untreated CLL/SLL

New Capabilities

Lilly's non-covalent BTK inhibitor expands from later-line therapy to first-line use for patients without 17p deletion

3 days ago: FDA approves Jaypirca for previously untreated CLL/SLL

Overview

Updated 1 hour ago

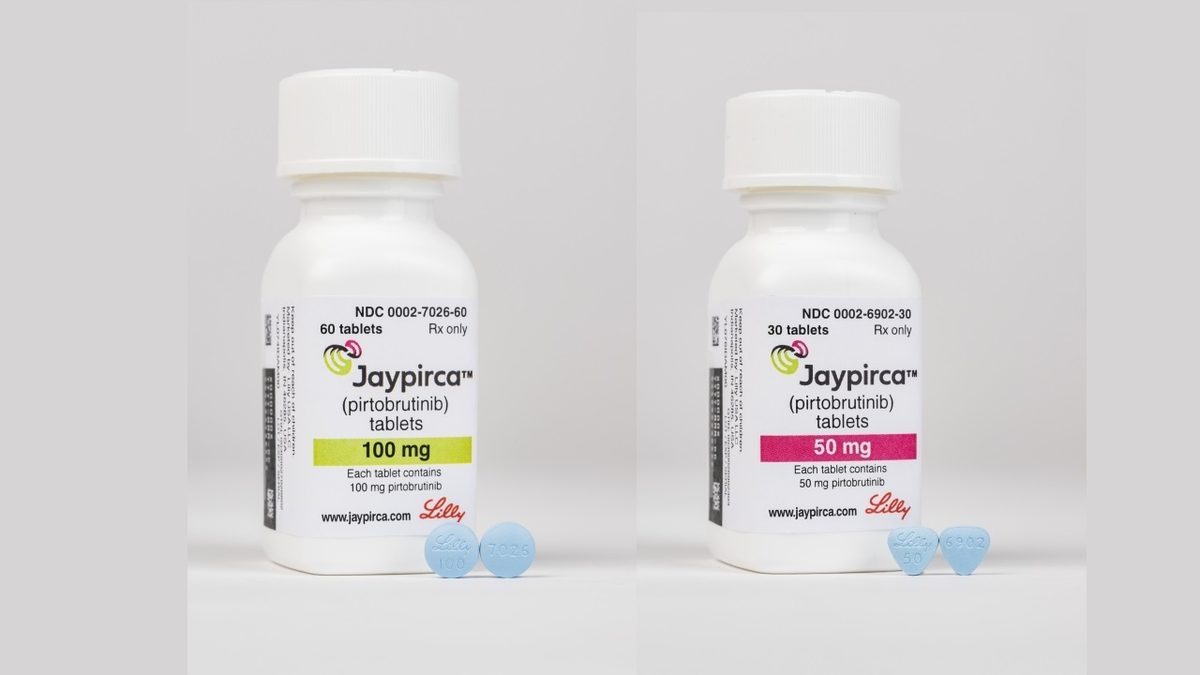
The FDA on October 2 approved Eli Lilly's Jaypirca for newly diagnosed chronic lymphocytic leukemia, making it the first non-covalent BTK inhibitor available as initial therapy. The approval covers adults with previously untreated CLL or small lymphocytic lymphoma who lack a 17p deletion, a subgroup that makes up roughly 92% to 95% of new cases.

Jaypirca joined ibrutinib, acalabrutinib, and zanubrutinib as the fourth BTK inhibitor cleared for first-line CLL, but with a key difference. It binds reversibly, so it stays effective when patients grow resistant to the covalent drugs. That durability creates a dilemma — use it now, or save it for when other drugs stop working.

Why it matters

First-line CLL treatment choices shape years of care; Jaypirca gives newly diagnosed patients a non-covalent option with a milder cardiac profile.

Questions about this story

Free account needed to ask — your question is kept and asked for you right after sign-up. Answers are public.

No questions yet — be the first to ask.

Key Indicators

0.20
Hazard ratio for progression or death vs chemoimmunotherapy
Median PFS not reached for pirtobrutinib vs 33.5 months for bendamustine plus rituximab at 28-month follow-up (p<0.0001)
94%
Overall response rate in pirtobrutinib arm
vs 81% for bendamustine plus rituximab in the BRUIN CLL-313 trial
28%
Serious adverse reaction rate
Serious reactions occurred in 28% of pirtobrutinib patients, most commonly pneumonia (5%)
4th
BTK inhibitors approved for first-line CLL
Jaypirca joins ibrutinib, acalabrutinib, and zanubrutinib in the first-line setting

Voices

Curated perspectives — historical figures and your fellow readers.

Ever wondered what historical figures would say about today's headlines?

Sign up to generate historical perspectives on this story.

People Involved

Organizations Involved

Timeline

May 2019 October 2026

5 events Latest: 3 days ago
Tap a bar to jump to that date
  1. FDA approves Jaypirca for previously untreated CLL/SLL

    Latest Regulatory

    Jaypirca becomes the first non-covalent BTK inhibitor available as first-line therapy for CLL/SLL patients without 17p deletion.

  2. BRUIN CLL-313 results presented at ASH, published in JCO

    Clinical Data

    Primary analysis shows pirtobrutinib cuts progression risk by 80% vs bendamustine plus rituximab in previously untreated CLL/SLL without 17p deletion.

  3. FDA approves Jaypirca for third-line CLL/SLL

    Regulatory

    Jaypirca is cleared for relapsed or refractory CLL/SLL in patients previously treated with a covalent BTK inhibitor, establishing the second-line position.

  4. FDA grants accelerated approval for relapsed mantle cell lymphoma

    Regulatory

    Jaypirca is approved for relapsed or refractory MCL after two prior lines of therapy, including a BTK inhibitor, on an accelerated basis.

  5. Lilly acquires Loxo Oncology, gaining pirtobrutinib

    Corporate

    Eli Lilly completes its roughly $8 billion acquisition of Loxo Oncology, obtaining the non-covalent BTK inhibitor then known as LOXO-305.

Scenarios

1

NCCN makes Jaypirca a preferred first-line option

Likely Resolves by End of 2027

Discussed by: Lilly executives and clinical investigators involved in BRUIN CLL-313; NCCN already lists Jaypirca as Category 2A for this population

The NCCN currently recommends Jaypirca as a Category 2A option for previously untreated CLL/SLL without del(17p), specifically for older patients with cardiac comorbidities. If uptake grows and guideline authors weigh the efficacy and safety data more heavily, they could upgrade it to Category 1 (preferred), placing it on equal footing with ibrutinib, acalabrutinib, and zanubrutinib. That would signal that doctors are using it early, not holding it in reserve.

2

FDA expands first-line label to include 17p deletion patients

Unlikely Resolves by End of 2028

Discussed by: MedPath trial database analysis noting roughly 5-8% of newly diagnosed CLL/SLL patients carry 17p deletion

The current label excludes patients with known 17p deletion, a high-risk genomic subgroup with worse outcomes. Expanding the indication would require new data from a trial that includes these patients, likely testing pirtobrutinib alone or with venetoclax in high-risk CLL. A positive readout would broaden Jaypirca's first-line reach to nearly all newly diagnosed patients.

3

Rival non-covalent BTK inhibitor reaches market, ending class monopoly

Possible Resolves by Q2 2028

Discussed by: Merck's nemtabrutinib program, another non-covalent BTK inhibitor in clinical development

Jaypirca is currently the only approved non-covalent BTK inhibitor, which supports its pricing power and its 'save it for later' rationale. If Merck's nemtabrutinib or another reversible BTK inhibitor wins FDA approval for CLL/SLL, doctors would gain a second option in the class, and Jaypirca's uniqueness would erode. Lilly's first-line positioning would then face direct competition within its own mechanism.

Historical Context

2 moments from history that rhyme with this story — and how they unfolded.

March 2016

Ibrutinib first-line CLL approval (2016)

Ibrutinib, the first covalent BTK inhibitor, won FDA approval for previously untreated CLL in March 2016 after the RESONATE-2 trial showed it beat chlorambucil in patients 65 and older. It marked the beginning of the end for chemoimmunotherapy as the CLL standard of care.

Then

Oral targeted therapy became the new first-line standard for many CLL patients within a few years.

Now

Ibrutinib and successor drugs turned CLL from a disease managed with chemotherapy into a chronically managed condition, opening the way for multiple BTK inhibitors to compete in the first-line setting.

Why this matters now

Jaypirca extends the same shift a decade later, but now the newcomer must compete with three established covalent inhibitors and justify early use rather than being held in reserve for resistant disease.

2006-2007

Second-generation TKIs in chronic myeloid leukemia (2006-2007)

Imatinib turned CML from a fatal leukemia into a chronic disease in the early 2000s. When patients relapsed on imatinib due to kinase mutations, dasatinib (approved 2006) and nilotinib (2007) were developed specifically to overcome those mutations.

Then

The new drugs rescued many imatinib-resistant patients and became additional options within the same drug class.

Now

Established the model of sequencing next-generation kinase inhibitors within a class and of designing successors to beat resistance mutations.

Why this matters now

Jaypirca plays the analogous next-generation role for BTK inhibitors, covering the C481S mutation that defeats covalent drugs — exactly why some doctors want to reserve it for later lines of therapy.

Sources

(6)