




Pull to refresh
Logo
Lundbeck trial shows VYEPTI helps migraine patients who failed other CGRP drugs

Lundbeck trial shows VYEPTI helps migraine patients who failed other CGRP drugs

New Capabilities

THRIVE trial primary endpoint: 60% of switchers reported significant improvement at week 24

Today: Lundbeck reports THRIVE headline results

Overview

Updated 1 hour ago

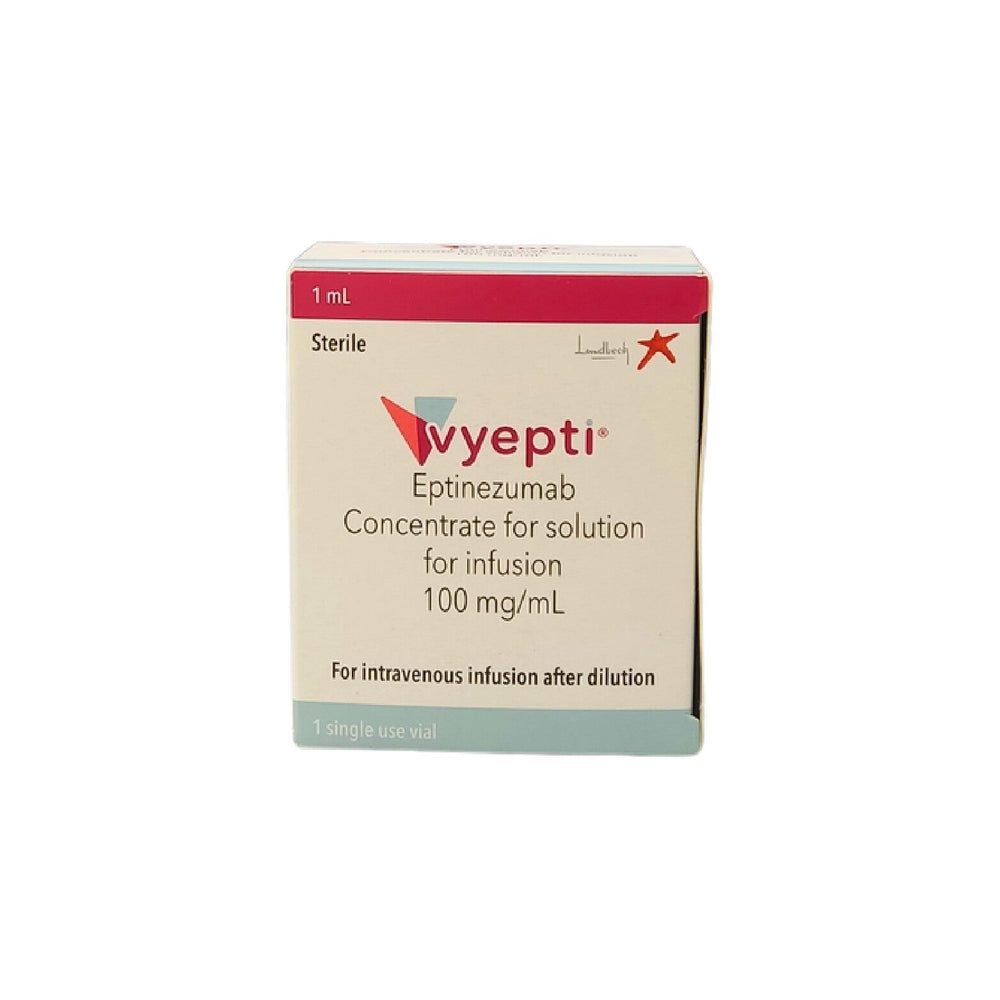
Migraine patients who try one CGRP-blocking drug and don't get relief now have evidence that switching to a different one can work. Lundbeck's Phase IV THRIVE trial found that after 24 weeks on VYEPTI (eptinezumab), 60% of participants reported being 'much improved' or 'very much improved.'

It's the first interventional trial to test eptinezumab specifically in patients who had an inadequate response to one prior CGRP-targeting preventive therapy. Before this, doctors had almost no data to guide what to prescribe next in that situation. No new safety signals appeared.

Why it matters

Patients who fail one CGRP migraine drug now have clinical evidence that switching to eptinezumab works — guidance that did not exist before.

Questions about this story

Free account needed to ask — your question is kept and asked for you right after sign-up. Answers are public.

No questions yet — be the first to ask.

Key Indicators

60%
Participants reporting 'much improved' or 'very much improved' at week 24
Primary endpoint of the THRIVE trial, measured on the 7-point Patient Global Impression of Change scale.
44%
Participants improved at week 12 on the 100 mg dose
Measured before dose escalation to 300 mg at week 12.
164
Adults enrolled in THRIVE
All had at least eight monthly migraine days and an inadequate response to one prior CGRP-targeting preventive.
84%
Trial completion rate
138 of 164 participants completed the 24-week trial.

Voices

Curated perspectives — historical figures and your fellow readers.

Ever wondered what historical figures would say about today's headlines?

Sign up to generate historical perspectives on this story.

Organizations Involved

Timeline

February 2020 October 2026

3 events Latest: Today
  1. Lundbeck reports THRIVE headline results

    Today Clinical Trial

    Phase IV trial shows 60% of participants with prior CGRP-therapy failure reported much or very much improvement at week 24.

  2. European Commission approves VYEPTI for migraine prophylaxis

    Regulatory

    Marketing authorization granted for adults with at least four migraine days per month.

  3. FDA approves VYEPTI (eptinezumab) for migraine prevention

    Regulatory

    Approval based on Phase III PROMISE-1 and PROMISE-2 trials, both of which cut monthly migraine days.

Scenarios

1

THRIVE full results confirm 60% response in peer-reviewed journal

Likely Resolves by End of 2027

Discussed by: Lundbeck and the academic migraine community (American Headache Society, European Headache Federation)

Lundbeck says it will present full THRIVE data at future congresses and submit them for peer-reviewed publication. If the published analysis matches the headline 60% responder rate and shows meaningful reductions in monthly migraine days, it becomes the reference evidence for treating patients who failed a first CGRP drug.

2

Headache societies add eptinezumab as a switch option in treatment guidelines

Possible Resolves by Q2 2028

Discussed by: Headache treatment guideline committees

Guideline bodies such as the American Headache Society or European Headache Federation periodically update prevention recommendations. THRIVE's data could earn eptinezumab an explicit recommendation for patients with inadequate response to a prior CGRP preventive — directly answering the sequencing question the trial was built to address.

3

Open-label design draws skepticism; adoption stalls without placebo-controlled data

Uncertain Resolves by End of 2028

Discussed by: Methodologists and evidence-based medicine commentators

THRIVE is open-label with no placebo arm, so some of the 60% response could stem from placebo effects or regression to the mean. If Lundbeck does not mount a placebo-controlled confirmatory study in prior-CGRP-failure patients, insurers and guideline panels may wait, limiting adoption despite the positive headline.

Historical Context

2 moments from history that rhyme with this story — and how they unfolded.

1991-2005

Triptan switching in acute migraine (1990s-2000s)

Neurologists documented that patients unresponsive to one triptan, such as sumatriptan, sometimes responded to another, like zolmitriptan or naratriptan. Clinicians built a practice of trying a second triptan after a first failed.

Then

Multiple triptans entered the acute migraine toolkit, each offering a distinct responder profile.

Now

Same-class switching became an accepted tool in migraine treatment, not an anomaly.

Why this matters now

Migraine care already embraces trying a second drug in the same class after failure; THRIVE extends that logic from acute relief to preventive CGRP therapy.

2003-2009

Anti-TNF switching in rheumatoid arthritis (2000s)

In the 2000s, trials such as GO-AFTER enrolled rheumatoid arthritis patients who had failed a tumor necrosis factor inhibitor and tested a different one. Many responded to the second drug despite failing the first.

Then

Within-class switching became standard rheumatology practice rather than a last resort.

Now

It established that a drug class can retain efficacy across its individual members, even after one member fails.

Why this matters now

THRIVE applies that same same-class switch model to CGRP-blocking migraine preventives, testing whether patients who fail one can still respond to another.

Sources

(5)